

The regulatory submission landed quietly, as these things often do. No patient recruitment drive. No clinical sites scrambling to meet enrollment targets. Just a computational model—Certara's Simcyp PBPK simulator, to be precise—predicting how asciminib, a chronic myeloid leukemia drug, would behave in human bodies under conditions that would have traditionally required ten separate clinical trials. In March 2026, the FDA said yes. The label updates went through based on the simulation alone.
It wasn't supposed to work this way. Not yet, anyway.
For years, digital twins of human biology occupied that frustrating middle ground between "promising research direction" and "something regulators might actually accept as evidence." The asciminib decision, according to those who've watched the space closely, marks a threshold crossing—the moment when validated computational models stopped being interesting supplements to real-world data and started, in certain contexts, replacing it entirely.
What makes the case particularly striking isn't just that it happened. It's that it barely made waves. The groundwork had been so thoroughly laid—through technical breakthroughs, regulatory guidance updates, and a string of smaller precedents—that accepting computational predictions as primary evidence felt almost inevitable. The healthcare digital twins market is projected to reach $69.67 billion by 2035 according to market research firm SNS Insider in a February 2026 report. That's the kind of trajectory that doesn't emerge from pure speculation.
The Ecosystem Taking Shape
Ask ten people what a healthcare digital twin actually is, and you'll get ten slightly different answers—which tells you something about where the field sits developmentally. At the most focused end, you have organ-specific simulators: virtual hearts that model electrical propagation patterns and mechanical stress; computational kidneys forecasting drug clearance rates based on renal function. At the other extreme are whole-patient twins—individualized simulations that ingest real-time data streams and attempt to predict disease progression or treatment response for a specific human being.
The market has already splintered into niches with clear leaders. Biosimulation platforms for pharmacokinetics—Certara's Simcyp, Simulations Plus's GastroPlus—dominate their corner, with the U.S. market alone projected to hit $9.82 billion by 2034 according to industry forecasts. HeartFlow, which generates coronary physiology models from CT angiography, has done something more impressive: it secured Centers for Medicare & Medicaid Services reimbursement codes worth roughly $1,017 per scan as of last year. Computational fluid dynamics became billable medicine.
Then there are the startups chasing direct patient applications. Twin Health, which raised $53 million in August 2025 at a reported valuation near $950 million, builds whole-body metabolic twins for diabetes reversal programs—the kind of thing that sounds slightly sci-fi until you look at the payer partnerships and measured outcome data they've started accumulating. Whether the model actually delivers on its promises at scale remains an open question, but the capital flowing in suggests investors think it's worth finding out.
The clinical trial space is where things get particularly interesting, and contentious. Unlearn, which secured European Medicines Agency qualification for its prognostic covariate adjustment methodology back in 2022, embeds AI-generated patient twins as external control arms—synthetic comparators that let sponsors shrink trial sizes or avoid placebos in certain contexts. This February, Unlearn partnered with VectorY on an ALS Phase 1/2 trial using digital twins as participant-level comparators. It's exploratory, and skeptics abound, but it would have been dismissed as fantasy five years ago.
QuantHealth, backed by Sanofi Ventures in an October 2025 investment, claims to have simulated over 350 clinical trials with 90% accuracy, crediting itself with $314 million in savings for a top-10 pharma client. Those are the kinds of numbers that always warrant a raised eyebrow—clinical trial validation is notoriously messy—but the fact that a major pharma corporate venture arm wrote a check says something about the hypothesis being taken seriously.
Why Regulators Started Saying Yes
The regulatory shift happened faster than many expected, which probably means the pain points had become unbearable. Clinical trial costs have spiraled into the tens of millions for complex programs, recruitment timelines stretch impossibly long for rare diseases, and the ethical discomfort of assigning sick patients to placebo arms keeps growing. Something had to give.
The FDA finalized guidance in November 2023 on assessing computational modeling credibility in medical device submissions—a framework rooted in the ASME V&V 40-2018 engineering standard, adapted for medical contexts. What's notable about the guidance is what it doesn't demand: perfection. Instead, it calls for rigor proportional to the model's intended use and the consequences of getting it wrong. A simulation predicting shelf life for a low-risk device faces different scrutiny than one informing implantable cardiac device design.
On the drug development side, the FDA's Model-Informed Drug Development program, running from fiscal 2023 through 2027, has institutionalized pharmacometric and systems pharmacology modeling across the product lifecycle. The agency disclosed in November 2024 that it had received over 500 submissions incorporating AI components since 2016—a volume that speaks to how commonplace these approaches have become, even if public attention tends to focus on the most dramatic cases.
Europe is moving in parallel. The European Medicines Agency put out a concept paper in February 2025 to develop formal guidelines for mechanistic models—PBPK, physiologically-based biopharmaceutics, quantitative systems pharmacology—used in drug development. That marks a shift from ad hoc acceptance to codified standards. Certara's achievement of EMA qualification for its Simcyp platform last August—the first PBPK software tool to receive such recognition—set a precedent. The asciminib case showed what that precedent looks like in practice.
Policy shifts helped pave the way, too. The FDA Modernization Act 2.0, signed in December 2022, explicitly enables alternatives to animal testing, including in silico methods. The EU AI Act, which entered force in August 2024 with high-risk provisions phasing in through 2027, imposes quality management and transparency requirements on patient-facing AI systems—including many clinical digital twins. These aren't frictionless green lights, but they legitimize computational approaches that existed in regulatory gray zones not long ago.
Proof Points Emerging Across Specialties
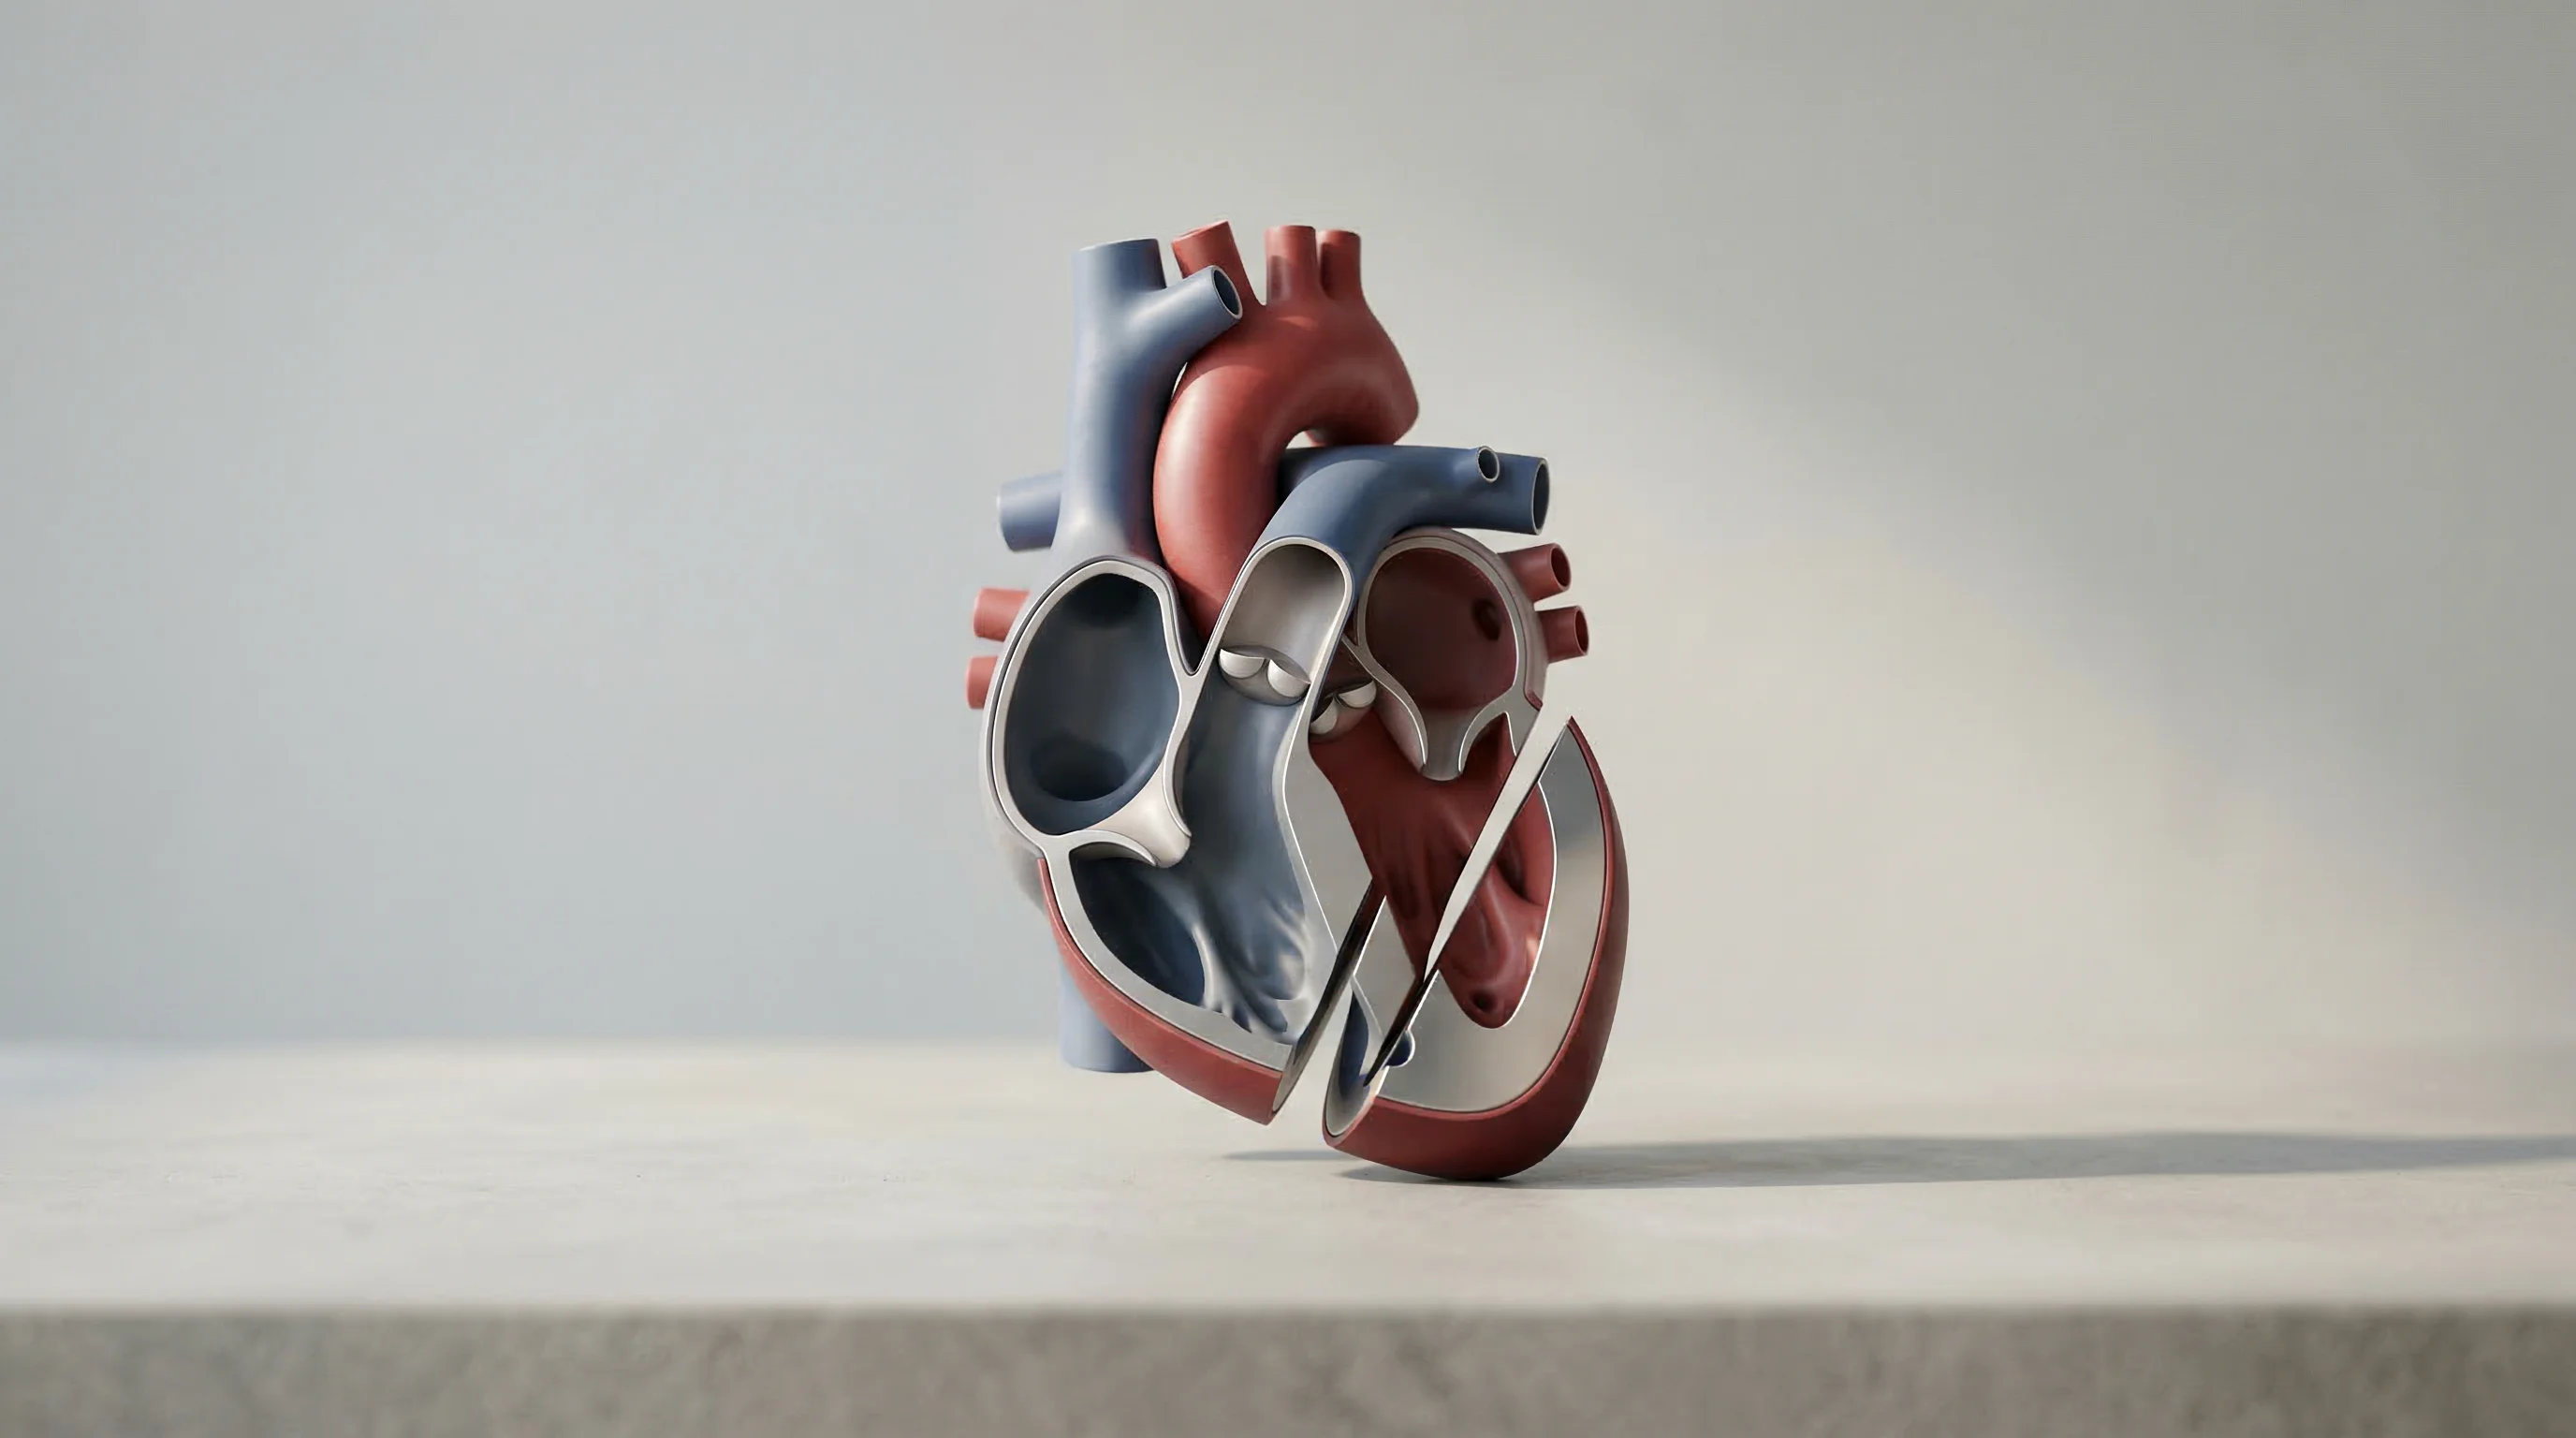
Cardiovascular medicine has generated the clearest success stories, perhaps because the physics are relatively tractable and the imaging infrastructure is mature. Dassault Systèmes' Living Heart Project, a multi-industry collaboration over a decade in the making, has evolved into an FDA-recognized tool for cardiovascular device review. The company announced last year it's entering a "next phase" with AI-powered virtual twins for risk prediction—though what that means concretely remains to be seen.
InHEART, a French startup that raised $11 million in May 2024, uses cardiac digital twins derived from MRI and CT scans to guide ablation procedures for arrhythmias. Electrophysiologists can visualize which tissue to target before threading a catheter into a patient's heart—pre-surgical planning that reportedly improves outcomes and shortens procedure times. It's the kind of application where the value proposition is straightforward enough that adoption doesn't require massive cultural shifts.
At a population scale, researchers released a preprint last May detailing cardiac digital twins built from roughly 55,000 UK Biobank MRI participants, complete with open tools for replication. That kind of infrastructure work—validated models, shared code, representative cohorts—matters more than any single flashy application. It's the unglamorous scaffolding future applications will build on.
Drug development use cases extend beyond cardiovascular, though validation remains patchier. Applied BioMath and Aitia (formerly GNS Healthcare) deploy quantitative systems pharmacology and network-based twins to identify targets and predict patient subgroups likely to respond. Aitia expanded its collaboration with Servier on glioma treatments through 2024-2025, using what it calls "Gemini Digital Twins" to simulate disease progression under various interventions. The results haven't been published in peer-reviewed journals yet, which makes independent assessment difficult.
Even hospital operations are getting the digital twin treatment—less about biology, more about throughput optimization. Siemens Healthineers showcased its "ActExcell Operational Twin" at the Radiological Society of North America meeting last December, promising real-time modeling of patient flow and equipment utilization. GE HealthCare published an October 2025 case study on digital twins changing hospital operations. These applications might seem tangential to drug development, but they train health systems to think computationally, and perhaps more importantly, they generate revenue while patient-level biological twins accumulate evidence.
The Validation Problem Nobody's Quite Solved
Technology isn't the bottleneck anymore—or at least, it's not the primary one. Deep learning can generate patient-level outcome predictions at scale; mechanistic organ models run fast enough on cloud infrastructure for clinical deployment. The hard part is proving those predictions are trustworthy for patients you've never seen, in subgroups underrepresented in training data, for rare diseases with sparse real-world evidence.
Academic reviews published in npj Digital Medicine through last year emphasize the need for transparent evaluation pipelines, post-deployment monitoring, and honest accounting of uncertainty. The October 2025 EDITH roadmap—a European multi-stakeholder blueprint for Virtual Human Twin infrastructure—calls for standardized data models, federated learning architectures respecting privacy, and regulatory harmonization across member states. These are the unsexy prerequisites for scale, the kind of infrastructure work that doesn't make headlines but determines whether digital twins remain niche tools or become standard practice.
Federated learning offers one potential path. The MELLODDY consortium, which united ten pharmaceutical companies in a study completed in 2024, demonstrated that collaborative machine learning can improve QSAR predictions without pooling proprietary datasets. Similar approaches could let digital twin developers train on diverse patient populations while keeping sensitive health records behind institutional firewalls—though the technical and governance challenges are non-trivial.
Interoperability standards are advancing, which matters more than it might sound. The U.S. Office of the National Coordinator for Health IT mandated updated SMART on FHIR capabilities by the end of last year; USCDI v3.1 was adopted in June 2025. Electronic health record data that's easier to extract, standardize, and feed into computational models makes real-time patient twins more feasible—or at least less nightmarishly difficult. The OMOP Common Data Model, widely used in research networks, is being mapped to primary care datasets like the UK's CPRD as of this March, expanding the observational evidence base that twins can draw from.
What the Next Phase Looks Like

For pharma and medtech executives, the strategic question isn't whether to engage with digital twins—that decision has arguably been made. The question is which bets to place and where to deploy resources. The asciminib case involved pharmacokinetics, arguably the most mature domain for computational prediction. What happens when quantitative systems pharmacology models for immunology, or biomechanical simulations for implantable devices, seek similar regulatory recognition? The EMA's forthcoming mechanistic model guideline, expected to move from concept paper to draft in the next year or two, will help define those boundaries.
Investors are placing bets across the entire stack. Twin Health's near-unicorn valuation reflects confidence in direct-to-patient applications; QuantHealth's Sanofi backing signals pharmaceutical interest in trial simulation; Quibim's €47.9 million Series A in January 2025 bets on imaging biomarkers as raw material for digital twins. Not all these companies will succeed—venture portfolios rarely work that way—but the capital deployment signals conviction that something substantial is emerging.
Clinical researchers and regulatory affairs professionals face a learning curve that shouldn't be underestimated. The FDA and EMA now expect sponsors submitting computational evidence to document context of use, model risk, verification and validation strategies, and uncertainty quantification—concepts borrowed from engineering that aren't standard in medical training. The FDA's Model-Informed Drug Development Paired Meeting Program, running through fiscal 2027, offers a venue for early dialogue. Companies that wait until late-stage development to engage may find themselves scrambling to retrofit validation studies.
Nobody serious is claiming digital twins will replace Phase 3 pivotal trials wholesale, at least not for novel indications where uncertainty runs high. But they're carving out territory in ways that were purely theoretical not long ago: reducing animal studies in preclinical phases, shrinking sample sizes through better-powered designs, replacing some drug-drug interaction or special-population studies with simulations, serving as external control arms where randomization is ethically fraught or logistically impossible.
Each regulatory acceptance strengthens the precedent. Each validated model becomes infrastructure for the next application. The asciminib decision this March mattered not because it was revolutionary in isolation, but because it demonstrated how much the foundation had already shifted beneath the industry's feet.
The real question—the one that will determine whether digital twins become standard practice or remain specialized tools—is how quickly the broader ecosystem can build what might be called "trust infrastructure." Regulatory bodies need frameworks for assessing model credibility across diverse use cases. Payers need evidence that computational predictions translate to real-world outcomes. Clinicians need interfaces that make simulation results interpretable at the point of care. Data custodians need legal clarity on model training and federated learning architectures.
That infrastructure is emerging, unevenly and sometimes chaotically. But the asciminib case suggests the timeline may be shorter than skeptics anticipated. When a major regulatory agency accepts simulations as primary evidence for label updates—not supplementary analysis, not supportive rationale, but the evidence itself—it's worth considering that the debate may have moved past "whether" and into "how quickly."
Human experimentation has always been the least satisfying answer to the question of how we prove medicines work. Digital twins won't eliminate that discomfort entirely. But they might, in time, reduce how often we have no alternative.


